

Advanced Regenerative Medicine
Advanced Regenerative Medicine
- The Goswami Clinic
Does Stem Cell Therapy Actually Work?
Stem cell therapy is designed to use the body’s own reparative cells to help calm inflammation and support tissue healing. Many patients report meaningful improvement in pain and function, but results vary by condition, cell type, and individual patient — and the treatment has not been evaluated by the FDA for most orthopedic uses.
Contact Us
How Is Stem Cell Therapy Meant to Work in the Body?
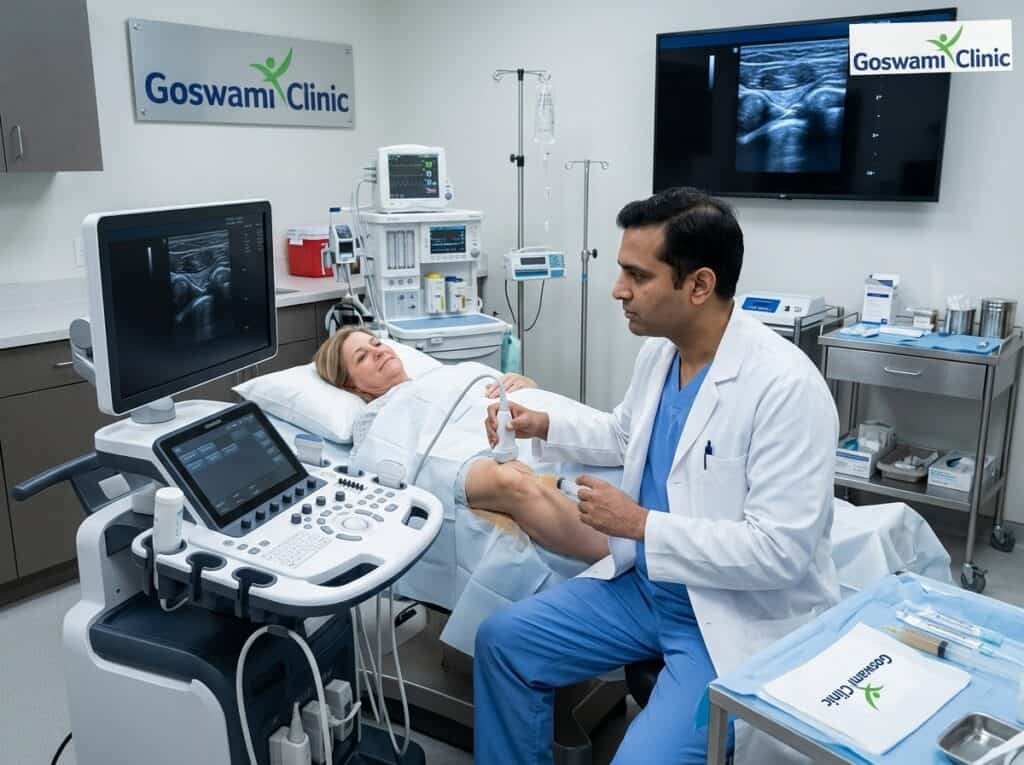
In most autologous protocols, cells are collected from a patient’s own bone marrow or fat tissue, concentrated, and then injected — typically under image guidance — into the injured or degenerated area, such as a joint affected by osteoarthritis or a degenerative spine condition.
Once in place, these cells are believed to act less like a physical replacement part and more like a signal. Research describes them releasing proteins — cytokines and growth factors — that can help modulate local inflammation, encourage nearby repair-oriented cells to migrate to the area, and support the surrounding tissue’s own healing machinery. Researchers sometimes call this a “paracrine effect.” It’s the leading theoretical model for how these treatments work, though the exact mechanism in any individual case can’t be observed directly, which is one reason results vary from patient to patient.
Contact Us
What Does the Current Research Actually Show?
Clinical research on stem cell therapy for orthopedic conditions has grown substantially over the past decade, with a number of studies reporting improvements in pain and function for patients with joint- and cartilage-related conditions. One widely cited meta-analysis published in npj Regenerative Medicine, which pooled 35 studies covering roughly 2,385 patients, reported significant improvements in knee pain, self-reported physical function, and cartilage quality following mesenchymal stem cell treatment — while also noting that the effect on cartilage volume specifically was limited.
A more conservative picture comes from the 2025 Cochrane living systematic review on stem cell injections for knee osteoarthritis, which pooled 25 randomized trials covering 1,341 participants. It concluded that stem cell injection may provide a small improvement in pain and function compared with placebo injection — but not in quality of life or overall treatment success — and that the clinical significance of that improvement remains unclear.
Those two findings are worth holding side by side rather than picking whichever is more flattering. Earlier meta-analyses have reported larger effects than Cochrane’s more tightly controlled placebo comparison, and the honest summary is that stem cell therapy shows real promise with genuinely mixed and still-developing evidence behind it. Any clinic that tells you the science is settled in either direction is overstating what is currently known.
That mixed picture is partly a function of how varied the research is. Study designs range from small case series to randomized trials, and cell source, dose, and outcome measures differ widely from one study to the next, which makes it difficult to compare results across studies or to quote a single statistic that applies to everyone. Conditions most frequently studied include knee osteoarthritis, tendon-related pain such as rotator cuff tendinopathy, and disc-related back pain. This remains an active and still-developing field, which is why an individualized conversation with your physician about the evidence for your specific condition matters more than a general number pulled from an unrelated study.
Who Tends to Respond Best to Stem Cell Therapy?
In general, patients with mild-to-moderate degenerative changes — rather than end-stage joint damage — tend to be considered better candidates, though this varies by condition and is never a hard rule. Overall health, activity level, and willingness to follow post-procedure guidance can also play a role in how someone responds. An accurate diagnosis, usually confirmed with imaging, is always the starting point before anyone discusses whether stem cell therapy for joint pain or a spine-focused approach makes sense for a given case.
What Can Make a Real Difference in Outcomes?
A few variables show up again and again in both the research and clinical experience: whether the injection is placed with image guidance rather than by feel, whether the cells used are autologous (your own) versus donor-derived, and the treating physician’s specific volume of experience with the procedure. Practices where the physician has trained extensively in these techniques — or trains other physicians in them — are generally further along that experience curve.
Some treatment plans also combine stem cell therapy with complementary approaches, such as PRP or peptide therapy, as part of a broader strategy rather than a single isolated injection. Whether combining approaches makes sense is an individualized decision your physician can walk you through.
Patient-side factors matter too. Following post-procedure activity guidance, maintaining a healthy weight where relevant, and addressing other contributing factors — such as overall joint alignment or the strength of the muscles surrounding the affected area — can meaningfully influence how well any regenerative treatment performs. This is one more reason a single injection is rarely presented as a complete, standalone solution rather than one part of a broader care plan.
What Are Reasonable Expectations to Set?
It helps to be realistic going in. Stem cell therapy is not a cure, and it shouldn’t be expected to reverse severe, advanced structural damage. A more reasonable goal for most patients is reduced pain and improved day-to-day function rather than complete elimination of symptoms. Improvement is typically gradual, unfolding over weeks to months rather than appearing immediately, and some treatment plans involve more than one session over time. Setting these expectations with your physician up front, based on your specific imaging and diagnosis, tends to lead to a much more satisfying experience than going in expecting a guaranteed fix.

How Is Success Typically Measured?
Rather than a single pass/fail outcome, most physicians and researchers track a combination of measures over time: self-reported pain scores, functional milestones such as walking distance or return to a specific activity, and sometimes follow-up imaging to see whether joint space or tissue appearance has changed. Because these measures are tracked over weeks and months rather than checked once, a single early follow-up visit usually isn’t enough to say definitively whether a treatment “worked” — which is part of why patience and consistent follow-up matter about as much as the procedure itself.
How Does Stem Cell Therapy Compare to Surgery or Cortisone Injections?
A cortisone injection can reduce inflammation and pain quickly, but the effect is generally temporary and doesn’t address the underlying tissue — and repeated cortisone use over time carries its own downsides that are worth discussing with your physician. Surgery, on the other hand, can be an effective option for advanced structural damage, but it involves an incision, anesthesia, and a real recovery period, and is generally considered after more conservative options have been tried.
Stem cell therapy sits as a middle path for appropriately selected patients who want to avoid or delay more invasive treatment. For patients specifically weighing their options against joint replacement, our alternative to knee replacement page walks through that comparison in more detail.
Frequently Asked Questions
How long does it take to know if stem cell therapy worked?
Healing is typically gradual rather than immediate. Many patients notice initial changes within a few weeks, with continued improvement reported over several months as the tissue responds. Your physician can give you a more specific timeline based on your condition.
Is stem cell therapy the same as PRP therapy?
No. Stem cell therapy uses reparative cells, usually from your own bone marrow or fat, while PRP therapy concentrates the platelets and growth factors already in your blood. The two are sometimes used together as part of one treatment plan.
Is stem cell therapy FDA-approved?
Most orthopedic stem cell therapies, including those offered here, have not been approved by the FDA. See the required disclosure above, and feel free to ask our team directly about the regulatory status of any specific treatment you’re considering.
Can stem cell therapy help me avoid joint replacement surgery?
For some patients with mild-to-moderate joint damage, it may help reduce symptoms and potentially delay the need for surgery, but it is not a guaranteed substitute for joint replacement in advanced cases. Our alternative knee replacement page discusses this comparison in more detail.
Will I need more than one treatment?
It depends on the individual and the condition being treated. Some plans call for a single session, while others are staged over time. This is determined through an individualized evaluation with your physician.
Does age affect how well stem cell therapy works?
It can be a factor, along with overall health and the severity of the condition being treated, though it isn’t the only consideration. Rather than ruling anyone out by age alone, most physicians weigh it as one part of a broader, individualized evaluation.
Curious whether stem cell therapy could be part of your care plan? Schedule a free phone consultation to find out.